Descrizione Clinica
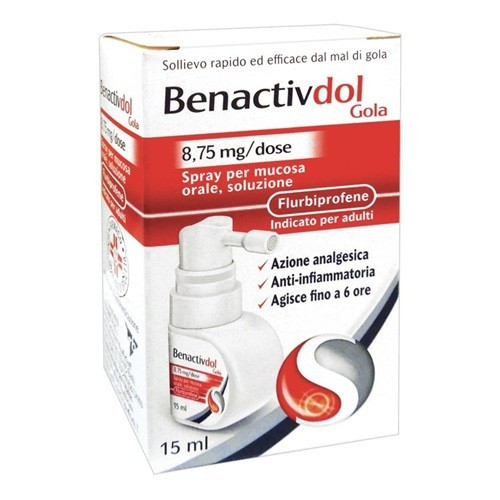
Disinfectants and antiseptics Benactivdolmed spray 15ml
BENACTIVDOLMED 8,75 MG/DOSE SPRAY FOR MUCOSA ORALE, SOLUTION
active ingredients
A 2,92 mg Flurbiprofene spray, a dose of three sprays contains 8,75 mg of Flurbiprofene, corresponding to 16,2 mg/ml of Flurbiprofene. Excipients with known effect: Benzoate parahydroxy (E218) 1,181 mg/dose Propile benzoate parahydroxy (E216) 0.2362 mg/dose The aromas contain allergens ( lemon aroma and honey aroma) For the full list of excipients, see paragraph 6.1.
Excellent
Betadex, Sodium phosphate dibasic dodecaidrate, Citric acid monohydrate, Metile parahydroxybenzoate (E218), Propile parahydroxybenzoate (E216), Sodium hydroxide, Aroma honey, Aroma lemon, N,2,3-Trimethyl-2-isopropylbutanamide, Saccarina sodium (E954). Qualitative composition of the Miele aroma: Flavoury substance/i, Preparation/i flavouring, propylene glycol (E1520). Limone aroma quality composition: Flavoury substance/i, Preparation/i flavouring, propylene glycol (E1520).
Therapeutic indications
Benactivdolmed is indicated for symptomatic treatment of short duration of acute pain in the throatache in adults.
Contraindications
• Hypersensitivity to the active ingredient or any of the excipients listed in paragraph 6.1. • Patients who have previously manifested hypersensitivity reactions (e.g. asthma, bronchospasm, rhinitis, angioedema or urticaria) in response to acetylsalicylic acid or other NSAIDs. • Peptic ulcer/recurring hemorrhage in place or pregress (two or more distinct episodes of demonstrated ulceration) and intestinal ulceration. • History of bleeding or gastrointestinal perforation, severe colitis, hemorrhagic or hematopoietic disorders related to a previous therapy with NSAIDs. • Last trimester of pregnancy (see paragraph 4.6). • Severe heart failure, severe kidney failure or severe liver failure (see paragraph 4.4). • Children and teenagers under the age of 18.
Population
Population: Only for short-term treatments. Adults from 18 years: a dose (3 sprays) administered at the back of the throat every 3-6 hours depending on the need, up to a maximum of 5 doses in a period of 24 hours. Pediatric population: The safety and effectiveness of Benactivdolmed in children or adolescents under the age of 18 have not been established. Senior Patients: A general posological recommendation cannot be provided, since clinical experience is limited to this day. The elderly have an increased risk of serious consequences in case of adverse reactions. You must administer the lowest effective dose for the shortest duration of treatment required to control symptoms (see paragraph 4.4). Method of administration: For oromucosal administration. Do not inhale during delivery. This medicine must be used for up to 3 days. Before first use, activate the pump, pointing the dispenser away from your body and spraying for at least four times, until you get the release of a fine and uniform nebulization. The pump is then activated and ready for use. Between use and use, point the dispenser away from your body and provide a minimum quantity of product, in order to ensure that the nebulization is fine and uniform. Before using the product always make sure the nebulization is fine and uniform.
Conservation
Do not refrigerate or freeze.
Warnings
Undesirable effects can be minimized using the lowest effective dose for the shortest duration of treatment needed to control symptoms. Infections: Since in isolated cases an exacerbation of infectious inflammations (e.g. development of necrotizing fascites) has been described in temporal association with the systemic use of drugs belonging to the class of NSAIDs, it is recommended that the patient immediately consult a doctor in case of the appearance or worsening of the signs of a bacterial infection during the treatment with flurbiprofene spray. You should consider whether the start of antibiotic therapy is indicated. In case of purulent bacterial pharyngitis/tonsilitis, the patient should consult the doctor for a reassessment of treatment. Treatment should be administered for up to 3 days. If symptoms worsen or new symptoms arise, treatment must be reassessed. If mouth irritation occurs, treatment with flurbirprofen should be suspended. Senior population: The elderly manifest an increased frequency of adverse reactions to the NSAIDs, especially bleeding and gastrointestinal perforation, which can be fatal. Respiratory effects: Bronchospasm may be precipitated into patients suffering or with a history of bronchial asthma or allergic disease. Flurbiprofen spray should be used carefully in these patients. Other: Using flurbiprofen spray should be avoided in conjunction with other NSAIDs, including selective cyclooxygenase-2 inhibitors (see paragraph 4.5). Systemic erythematous lupus (LES) and mixed connective tissue disease: Patients with systemic erythematosum lupus (LES) and mixed connective tissue disease may have an increased risk of aseptic meningitis (see paragraph 4.8), however this effect is not usually observed with products intended for limited and short-term use as flurbiprofen spray. Comprogation of cardiovascular, kidney and liver: It has been reported that NSAIDs can cause various forms of nephrotoxicity, including interstitial nephritis, nephrosic syndrome and kidney failure. The administration of an NSAID can cause a dose-dependent reduction in prostaglandine formation and decrease kidney failure. Patients with greater risk of developing this reaction are those with compromised kidney function, heart failure, liver dysfunction, those in diuretic therapy and the elderly; however, this effect is usually not observed with products intended for limited and short-term use such as flurbiprofen spray. Hepatitis effects: Hepatic mild to moderate dysfunction (see paragraph 4.3 and 4.8). Cardiovascular and cerebrovascular effects: Before starting treatment in patients with anamnesi of hypertension and/or heart failure, caution is required (return to the doctor or pharmacist) since retention of fluid, hypertension and edema were found in association with NSAID therapy. Clinical studies and epidemiological data suggest that the use of some NSAIDs (especially at high doses and long-term treatment) may be associated with a slight increase in the risk of arterial thrombotic events (e.g. myocardial or stroke infarction). There is not enough data to exclude this risk with flurbiprofen when administered at a daily dose not exceeding 5 doses (3 dispenses per dose). Effects on the nervous system: Cephalea induced by analgesics - In case of prolonged or uncontrolled use of analgesics, cephalea can be manifested, which should not be treated by increasing the dose of the medicinal product. Gastrointestinal effects: NSAIDs should be administered with caution to patients with a gastrointestinal disease anamnesi ( ulcerative colitis, Crohn's disease) since these conditions can be exacerbated (see paragraph 4.8). Blood, ulceration or gastrointestinal perforation, which can be fatal, have been reported with all NSAIDs at any time during treatment, with or without warning symptoms or a previous anamnesi of serious gastrointestinal events. The risk of gastrointestinal bleeding, ulceration or perforation is higher with the increase in doses of NSAIDs, in patients with ulcer anamnesi, especially if complicated by hemorrhage or perforation (see paragraph 4.3) and in the elderly; however, this effect is usually not observed with products intended for a limited use of short duration as flurbiprofen spray. Patients with a gastrointestinal toxicity analogy, especially if elderly, should report any unusual abdominal symptoms (especially gastrointestinal bleeding) to their attending physician. Caution should be recommended in patients receiving concomitant medicines that can increase the risk of ulceration or bleeding, such as oral corticosteroids, anticoagulants such as warfarin, selective inhibitors of serotonin reuptake or pyasternic anti-aggregants such as acetylsalicylic acid (see paragraph 4.5). If bleeding or gastrointestinal ulceration occurs in patients who are taking flurbiprofen, treatment must be stopped. Ematologic effects: Flurbiprofen, like other NSAIDs, can inhibit piastrinic aggregation and prolong bleeding time. Flurbiprofen spray should be used with caution in patients with potential abnormal bleeding. Dermatory effects: Severe skin reactions, some of which fatal, including exfoliative dermatitis, Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported very rarely in association with the use of NSAIDs (see paragraph 4.8). Flurbiprofen spray must be suspended at the first appearance of skin rash, mucosa lesions or any other sign of hypersensitivity. This product contains parahydroxybenzoate methyl and parahydroxybenzoate propile that can cause allergic reactions (sometimes also delayed). This product contains less than 1 mmol (23 mg) of sodium per dose, i.e. essentially “without sodium”. Aromas containing allergens: This product contains aromas in turn containing anisilic alcohol, citral alcohol, citronellol, d-Limonene, geranium and linalol. Anisilic, cytral, citronellol, d-Limonene, geranium, linalol may cause allergic reactions.
Interactions
| The Flurbiprofen must be avoided in association with: | |
| Other NSAIDs including selective oxygenase-2 inhibitors: | Avoid the concomitant use of two or more NSAIDs, as this can increase the risk of adverse effects (especially gastrointestinal adverse events such as ulcers and bleeding) (see paragraph 4.4). |
| Acetylsalicylic acid (low doses): | Unless intake of aspirin at low doses (not more than 75 mg/die) has been recommended by the doctor, since the risk of adverse events could increase (see paragraph 4.4). |
| Flurbiprofen should be used with caution in association with: | |
| Antiagulants: | NSAIDs can enhance the effects of anticoagulants such as warfarin (see paragraph 4.4). |
| Anti-platelet aggregates: | There is an increased risk of gastrointestinal ulceration or bleeding (see paragraph 4.4). |
| Antihypertensive drugs (Diuretics, ACE inhibitors, angiotensin antagonists II): | NSAIDs can reduce the effect of diuretics and other antihypertensive drugs can enhance neurotoxicity caused by cyclooxygenase inhibition, especially in patients with impaired kidney function. |
| Alcohol: | It can increase the risk of adverse reactions, especially bleeding in the gastrointestinal tract. |
| Heart glycosides: | NSAIDs can exacerbate heart failure, reduce VGR (glomerular filtration speed) and increase plasma levels of glycosides - adequate control is recommended and, if necessary, a dose adjustment. |
| Ciclosporin: | There is an increased risk of nephrotoxicity. |
| Courtesy: | There is an increased risk of gastrointestinal ulceration or bleeding (see paragraph 4.4). |
| Litio: | There may be an increase in serum levels of lithium - adequate control is recommended and, if necessary, a dose adjustment. |
| Metotress: | The administration of NSAIDs within 24 hours prior to or after the administration of metotressate may lead to high concentrations of metotressate and to an increase in its toxic effects. |
| Mifepristone: | NSAIDs should not be used for 8 to 12 days after mifepristone administration, as NSAIDs can reduce the effect of mifepristone. |
| Oral antidiabetics: | Alterations of blood glucose levels have been reported (it is recommended to increase the frequency of controls). |
| Fenitoin: | Serum levels of phenytoin can increase - adequate control is recommended and, if necessary, a dose adjustment. |
| Diuretic potassium savers: | Concurrent use can cause hyperkaliemia. |
| Probenecid and Sulfinpirazone: | Medicines containing probenecid and sulfinpirazone may delay the excretion of flurbiprofene. |
| Chinolonic Antibiotics: | Animal data indicate that NSAIDs can increase the risk of convulsions associated with chinolonic antibiotics. Patients taking NSAIDs and kinolones may experience an increased risk of developing seizures. |
| Selective serotonin reuptake inhibitors (SSRI): | There is an increased risk of gastrointestinal ulceration or bleeding (see paragraph 4.4). |
| Tacrolimus: | An increased risk of nephrotoxicity is possible when NSAIDs are administered along with tacrolimus. |
| Zidovudina: | There is an increase in the risk of hematological toxicity when NSAIDs are administered along with zidovudine. |
Pediatric population: Additional information is not available.
Effects
Hypersensitivity reactions to NSAIDs have been reported and these can consist of: (a) non-specific allergic reactions and anaphylaxis; (b) reactivity of the respiratory tract, for example asthma, aggravated asthma, bronchospasm, dispnea; (c) various skin reactions, such as itching, hives, angioedema and, more rarely, exfoliative and bollous dermatosis (including epidermal necrolysis and multiform erythema). Edema, hypertension and heart failure were reported in association with treatment with NSAIDs. The data is insufficient to exclude this risk by using flurbiprofen spray for oral mucosa, solution. The list of adverse effects reported below refers to those recorded with flurbiprofen, used at doses compatible with the OTC classification and for a short period. (Very common (≥1/10), Common (from ≥1/100 to Emolinfopoietic System Pathologies. Not known: anemia, thrombocytopenia. Cardiovascular and cerebrovascular diseases. Not known: edema, hypertension, heart failure. Diseases of the nervous system. Municipality: capogiro, cefalea, parestesia; Not common: drowsiness. Respiratory, chest and mediastinic pathologies. Common: irritation of the throat; Not common: exacerbation of asthma and bronchospasm, dispnea, sibilant breathing, vesicular eruption oropharyngeal, hypoesthesia of pharynx. Gastrointestinal diseases. Common: diarrhea, mouth ulceration, nausea, oral pain, oral paresthesia, oropharyngeal pain, oral discomfort (heat or burning sensation, mouth tingling); Not common: abdominal abdomen, abdominal pain, constipation, dry mouth, dyspepsia, flatulence, glossodinia, dysgeusia, oral disestesia, vomiting. Pathologies of skin and subcutaneous tissue. Not common: rashes of various types, itching; Not known: severe forms of skin reactions such as boiling reactions, including Stevens-Johnson syndrome and toxic epidermal necrosis. General pathologies and conditions for administration. Not common: pyrexia, pain. Immune system disorders. Rare: anaphylactic reaction. Psychiatric disorders. Not common: insomnia. Hepatobiliary diseases. Not known: hepatitis. Reporting of suspicious adverse reactions. The reporting of suspicious adverse reactions that occur after the authorization of the medicinal product is important, as it allows continuous monitoring of the benefit/risk ratio of the medicinal product. Healthcare workers are required to report any suspected adverse reaction via the national reporting system at the address https://www.aifa.gov.it/content/segnalazioni-reazioni-avverse.
Overdosing
Synonyms Most patients who have ingested clinically important quantities of NSAID will develop no more than nausea, vomiting, epigastric pain, or more rarely diarrhea. Tinnitus, headache and gastrointestinal bleeding are also possible. In cases of more severe intoxication by NSAIDs, toxicity is observed at the expense of the central nervous system, which is manifested with drowsiness, occasionally excitement, blurred vision and disorientation or coma. Occasionally patients develop seizures. In severe intoxication from NSAIDs, metabolic acidosis can occur and protrombine/INR time can be prolonged, probably due to interference with the action of circulating coagulation factors. Acute kidney failure and liver damage can occur. Asthma exacerbation is possible in asthmatic subjects. Treatment The treatment must be symptomatic and supportive and must include the maintenance of airway pervity and the monitoring of heart function and vital signs until stabilization. The oral administration of activated charcoal or gastric lavender should be taken into account and, if necessary, correction of serum electrolytes if the patient occurs within an hour of ingestion of a potentially toxic quantity. Convulsions, if they are frequent or prolonged, must be treated with diazepam or lorazepam intravenously. Administer bronchodilators for asthma. There is no specific antidote for flurbiprofen.
Pregnancy
: Inhibition of prostaglandin synthesis can negatively affect pregnancy and/or embryo/fetal development. The data obtained from epidemiological studies suggest an increase in the risk of abortion, heart malformation and gastroschisis following the use of an inhibitor of the synthesis of prostaglandins at the beginning of pregnancy. The absolute risk of cardiovascular malformation had increased from less than 1% to approximately 1.5%. It is believed that the risk increases with dose and duration of therapy. In animals, it has been shown that the administration of a prostaglandin synthesis inhibitor causes an increase in pre- and post-system losses and embryo-fetal lethal. In addition, an increased incidence of various malformations, including cardiovascular malformations, was reported in animals that had been given an inhibitor of prostaglandin synthesis during the organogenetic period. Flurbiprofen should not be administered during the first and second trimester of pregnancy. During the third trimester of pregnancy, all prostaglandin synthesis inhibitors can expose • fetus to: - cardiopulmonary toxicity (with premature closure of arterial duct and pulmonary hypertension); - kidney dysfunction that can progress towards kidney failure with oligo-idramnios; • the mother and the newborn, at the end of pregnancy, to: - possible prolongation of bleeding time, an anti-aggregating effect that can occur even at very low doses. - inhibition of uterine contractions resulting in delay or extension of labor. As a result, flurbiprofen is contraindicated during the third trimester of pregnancy (see paragraph 4.3).
Food
: In a limited number of studies, flurbiprofen appears in breast milk at very low concentrations and is unlikely to have adverse effects on breast-feededed infant. However, due to the possible adverse effects of NSAIDs on breast-feeding infants, it is not recommended to use flurbiprofen spray by nursing mothers.
Fertility
: There are some evidence indicating that prostaglandin cyclooxygenase/synthesis inhibitors can cause female fertility to be compromised by an effect on ovulation. This is reversible as a result of termination of treatment.
Source: Farmadati